Industries
Healthcare acoustics
Hospitals are noisy buildings, and most of the people in them know it. Around 86 percent of patients report their rooms are noisy, and two thirds of healthcare workers say the same about their workplace. Much of it is preventable. Noise in a care environment affects rest and recovery, adds to staff fatigue, and interferes with the communication clinical work depends on.
What comes up most
The spaces fight each other.
A patient room has to be quiet enough to sleep in, private enough for a clinical conversation, and open enough that staff hear what they need. Infection control rules out many of the finishes that would resolve it.
Headwalls.
Services entering through the headwall are a recurring source of sound isolation failure at commissioning, particularly where headwalls back onto each other.
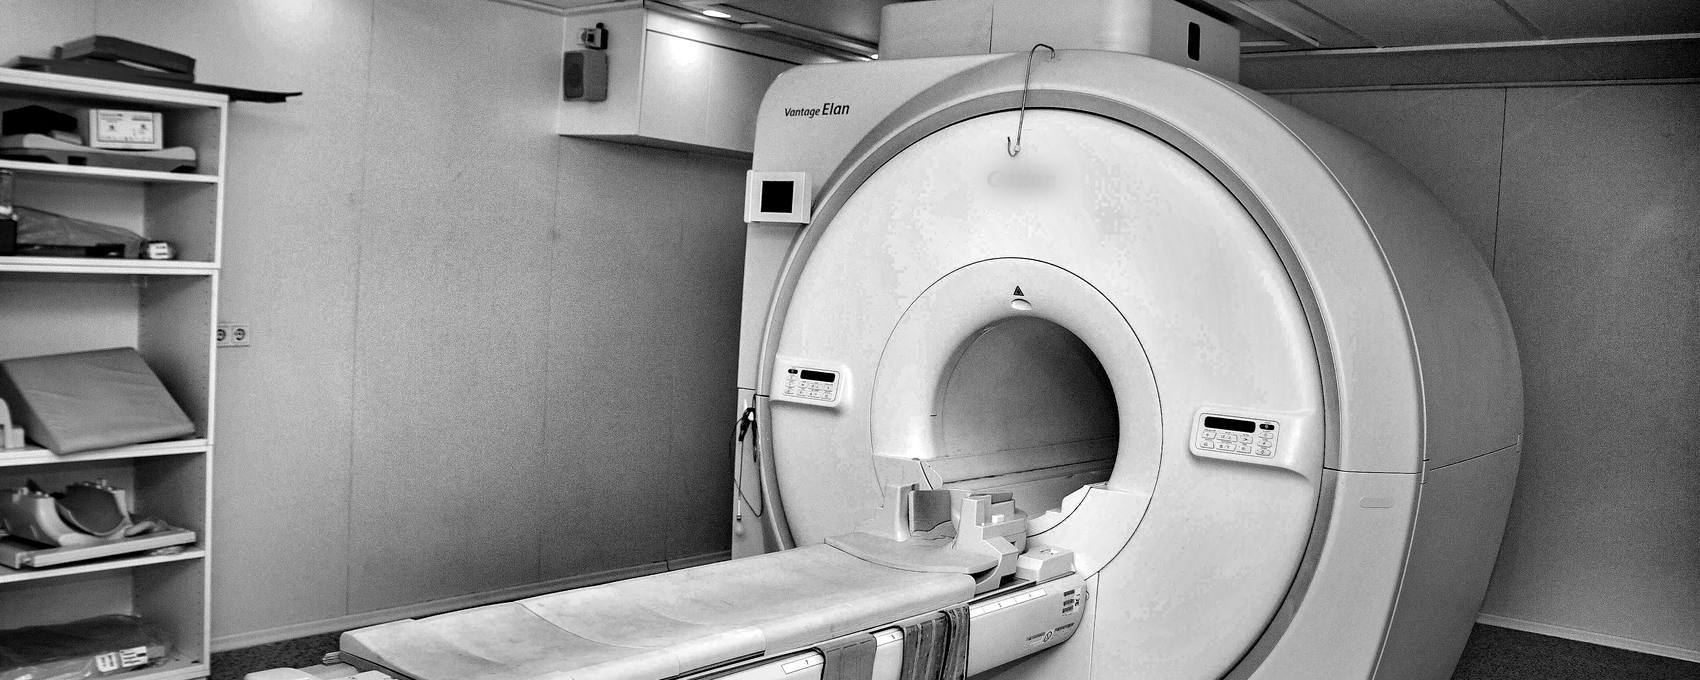
Imaging and vibration.
Diagnostic imaging is placed for clinical adjacency, not for vibration, which puts sensitive equipment near loading docks, parking, plant or rail. The manufacturer’s limit has to be confirmed, not assumed.
Shielded rooms.
MRI suites and radiation bunkers layer acoustic requirements onto RF shielding, structural reinforcement and dense services. The coordination is the hard part.
Constrained sites.
Healthcare land is often what was available, so generators, heliports, neighbouring industry, rail and road end up closer than anyone would choose.
The aging population.
Hearing loss accelerates with age, and noise contributes to confusion in older patients. A background level that suits a general population may not suit the people who use the building most.
Building on an active site
Most new healthcare capacity in Ontario is added to sites already in use, which creates two problems a greenfield project does not have.
In planning.
Environmental noise limits apply to the whole site, not the new building alone. A new central plant is assessed alongside the existing plant and generators, so a facility compliant on its own may not be once the addition is in. Better known before the site plan is fixed.
During construction.
The hospital next door keeps operating through demolition, excavation and structural work. That takes limits set against what the facility actually needs, monitoring that warns rather than records, and a working relationship with the people running the building.
Our engineers’ experience
Bentham’s engineers have worked as acoustical consultants on healthcare projects across Canada, on both sides of the table: designing and delivering hospitals for design-build teams, and representing authorities on the compliance side. Having done both is what lets you sit with an owner and a builder, explain what a decision costs each of them, and reach an answer everyone can live with.
Some of that work:
From full acute care to a single department.
The work runs from full acute care hospitals, carried from output specification through design, construction review and verification testing, down to cancer centres, imaging and surgical suites, clinics and single departmental renovations. Most of it on sites that could not stop working.
Building between two live buildings.
One project inserted a new facility between two operating buildings, with a CT scanner in the basement nearest the excavation. The same scope covered the operating rooms, labour and delivery, laboratories and the imaging suite above. That is the shape of most healthcare work now: a live clinical environment and a construction sequence that has to bend around it.
Verification is won months earlier.
Rooms verify at commissioning because of what happened months before: details coordinated, submittals reviewed, site visits where something was caught while it could still be fixed. The verification record is a product of that work rather than of anything that happens on the day.
Bentham Acoustics is new. Its engineers are not. The projects described here were carried out by Bentham engineers over their careers, at this firm and before it.
A full list of relevant project experience is available on request.
Standards and requirements in Ontario
Several documents apply at once, and none sets a single target that covers every space.
CSA Z8000.
The national standard for Canadian health care facilities. Criteria for sound isolation and background noise, alongside broader design guidance.
FGI Guidelines.
The American framework, frequently referenced on Canadian projects. Covers exterior noise, finishes, room noise, sound isolation, speech privacy and vibration.
The project’s own specification.
On a P3 or Infrastructure Ontario project this usually governs. It may reference CSA, FGI, both, or numbers of its own.
Vibration.
Set by the equipment manufacturer rather than by a standard. Limits vary between vendors and between models, and are often confirmed later than the structural design would like.
Where the risk usually sits
The number is the easy part.
Requirements arrive as figures: STC 60 on a partition, a background level in a room schedule. What decides whether the finished room performs is the detailing underneath them, the penetrations, the door seals, the way the partition meets the deck.
Solutions the whole team can build.
An acoustical detail sits alongside structural depth, mechanical routing, infection control, clinical adjacency and cost. A recommendation that answers only the acoustic question will not get built.
Prove it before it is repeated.
A hospital builds the same room hundreds of times. A mockup with real walls, HVAC, doors and finishes shows what the detail achieves while there is still time to change it.
Commissioning finds what design missed.
The failures that show up in testing are rarely the partition itself, but a gap at a penetration, adhesive spacing on laminated drywall, headwalls placed back to back.